This Changes Everything About Predicting Heart Attacks
In a Nutshell
The core message is that AI-powered plaque analysis on coronary CT angiography is now the best predictor of heart attack and stroke risk—far superior to calcium scores, stress tests, cholesterol panels, or CRP—because it directly measures unstable soft plaque and arterial wall inflammation via fat attenuation index. The study of 453 patients showed soft plaque percentage (18% vs 12%) predicted cardiac events while CRP and calcified plaque showed no difference between groups. The key takeaway is "test, don't guess": use this imaging approach to identify actual plaque risk, then address root causes like insulin resistance through lifestyle changes rather than relying on standard risk factors.
These notes were generated by AI and may contain inaccuracies.
A new study found there's a better way to predict heart attack and heart attack risk that's way better than a stress test, way better than a calcium score, and way better than a cholesterol panel. For people in their 60s or 70s with plaque in their arteries and high cholesterol, this test can definitively determine actual risk level.
Arterial plaque and inflammation matter far more than cholesterol and plumbing. The test has been recommended for years, but research evidence has now caught up with clinical observations.
The discussion covers what the test is and what it measures, findings from the newest study on this test released this year, and live questions from viewers.
Dr. Brewer ran the preventive medicine program at Johns Hopkins, training doctors on disease prevention. He now helps people avoid heart attacks, strokes, and early death. The show content is educational only, not medical advice.
Viewers can call 888-632-6163 with questions about heart attacks, strokes, or preventive medicine.
Inflammation, mostly driven by metabolic disease and pre-diabetes, is a major cause of heart disease. Inflammation must be measured correctly using a combination of blood markers that measure vascular inflammation and direct visualization of plaque inside arteries.
Blood tests and direct imaging answer different questions. The new technology adds the ability to see inflammation in the artery itself, not just plaque presence.
Eating causes blood sugar spikes followed by insulin floods. Both damage the endothelium, the smooth inner lining of arteries. The glycocalyx is a slick, easily injured part of this lining. Soft plaque builds underneath, the dangerous unstable kind that cracks open and causes clots leading to heart attacks or strokes.
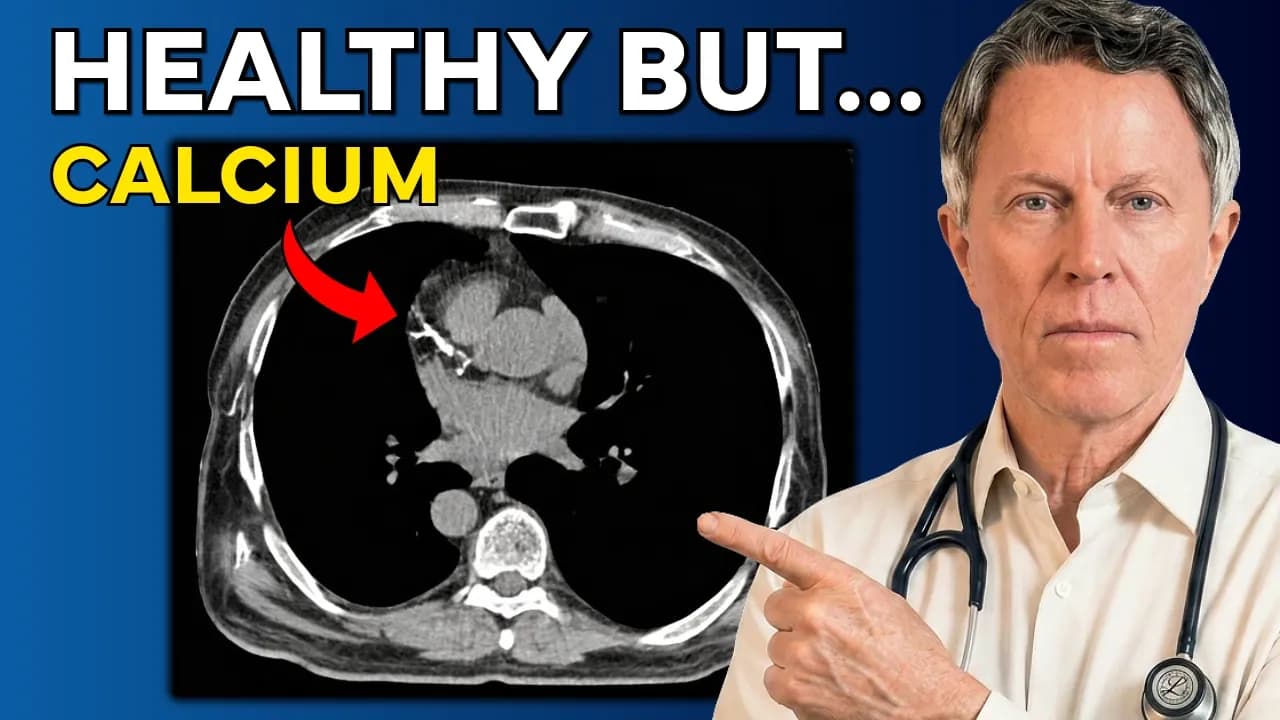
Soft plaque has mucus-type consistency that can break off, triggering clot formation. Hard calcified plaque is older, more stable, and doesn't cause risk by itself. The Honda study showed hard plaque serves only as a marker for potential soft plaque.
The test has been available for over a decade but only recently utilized. Inflammatory signals from artery walls affect surrounding fat. Each coronary artery is wrapped in a sleeve of fat whose composition changes based on inflammation.
When fat gets inflamed, it becomes more watery and less lipid-rich. Inflamed fat reads brighter than quiet fat on CT scans. FAI measures how bright something appears on imaging. The test reads the "stain" on the fat sleeve around arteries, similar to detecting leaks behind drywall.
A study across eight hospitals found people with inflammation in all three coronary arteries had dramatically higher risk of dying from heart disease. The test predicted major adverse cardiovascular events (MACE) independently of usual risk factors and independently of visible disease on scans. It identified risk even in people with no visible plaque and calcium scores of zero.
A study of 453 people with diagnosed heart disease used coronary CT angiography (CCTA/CTA) with dye. Images were analyzed using artificial intelligence software measuring fat attenuation index at the worst narrowing spot, throughout the rest of each artery, and total plaque amounts by type (calcified vs soft).
Typical CTA with AI focuses on flow/plumbing, which doesn't predict risk. The plaque analysis approach measures soft plaque amounts. After three years, 103 of 453 participants had heart attacks, heart failure, or worse outcomes.
High-sensitivity CRP was 4.7 in the event group and 4.9 in the healthy group, showing no predictive value. CRP has too many false positives to depend on alone, though it remains useful as part of a panel.
People with events had roughly 18% soft plaque versus 12% in the healthy group. Hard calcified plaque was 22% versus 21%, showing minimal difference. Soft plaque separated the groups more than any other measurement. Inflamed plaque tracked with soft plaque, not calcium.
CTA with AI plaque analysis is now the best available method for assessing arterial plaque risk for heart attack and stroke. It's not the only approach but forms the foundation for risk assessment.
Challenges include cost, insurance coverage issues, dye injection requirements, radiation exposure, stent compatibility concerns, and need for controlled heart rate during scanning. Insurance often doesn't cover the test.
A person following all recommended advice for 30 years, including Mediterranean diet with excessive grapes and grains, could receive a clean report while being three years from a fatal event. Testing beats guessing.
The protocol starts with "test, don't guess" by examining arteries directly, not just blood markers, then addressing underlying drivers like post-meal glucose spikes and insulin resistance.
Dr. Jesus Vega joins the discussion, noting that both coronary CT and AI analysis are expensive when paid out of pocket, requiring IV dye and analysis by specialized companies.
A new CPT code now exists for insurance billing. Medicare and certain insurance companies are beginning to cover the test. Companies providing FDA-approved AI analysis include HeartFlow, Cleerly, Elucid, and recently Kyrie Heart from the UK.
Many providers focus on fractional flow reserve rather than plaque analysis. These are different reports. The density measurement is critical for identifying soft plaque, which appears as low-density, soft, black areas with fat and water infiltration.
The latest study shows soft plaque presence on AI analysis is a better predictor of cardiac events than cholesterol or elevated high-sensitivity CRP. A panel of inflammation markers should be used, not just CRP, combined with plaque analysis.
Carotid ultrasound can identify soft plaque as a starting point. For deeper assessment, CTA with AI plaque analysis is recommended.
Dr. Vega advocated for this testing approach two years ago when Dr. Brewer was initially skeptical, correctly predicting it would become significant.
CIMT detects soft plaque as well as mixed calcified plaque. While comfortable with CIMT previously, AI analysis on CTAs represents a new gold standard for plaque evaluation.
Mary from Illinois asked about risk factors including high Lp(a), ApoB, low HDL, and how to address them.
ApoB is the protein used to make LDL and other plaque-forming particles including remnant cholesterol and chylomicrons.
Lp(a) is similar to LDL with genetic variations in the Apo protein. It's a major risk factor for heart attack and stroke, though often ignored due to beliefs nothing can be done. Levels much higher than 40 are more significant than lower elevations.
HDL levels of 40 or lower are associated with major cardiovascular risk. The current debate centers on whether LDL, ApoB, low HDL, or Lp(a) are causative or merely associated with risk. Dr. Brewer tends toward the association view.
Dr. Brewer acknowledges that while some components may be causative, he avoids deep debate on this topic. As a 69-year-old man with plaque and a practicing physician seeing patients daily, he emphasizes that 100% certainty is rarely achievable in preventive medicine. He references physicist Richard Feynman, noting that science operates with varying levels of certainty rather than absolute certainty, and practitioners must act on probabilities.
The fundamental issue identified is that preventive medicine continues to focus on the wrong targets. Plaque analysis offers a more effective approach than current standard practices.
Alyssa, diagnosed with supraventricular tachycardia (SVT) and taking metoprolol, reported breakthrough episodes with blood pressure readings as high as 220 over 125. She was advised by emergency room staff to only check blood pressure when feeling well, which she found unhelpful.
The advice to check blood pressure when relaxed has merit, as readings taken during stress, activity, or bathroom needs may not reflect baseline pressures. However, this guidance doesn't address underlying challenges that need management.
SVT refers to fast heartbeat originating from chambers above the ventricles. Atrial fibrillation represents the most common type, along with atrial flutter. These arrhythmias are strongly associated with undiagnosed pre-diabetes and constitute a major stroke risk factor.
For atrial fibrillation and SVT, brain protection should be the primary focus rather than heart protection, due to elevated stroke risk. Electrophysiologists emphasize this priority ordering. Many patients with these conditions lack proper stroke risk management.
Prevention depends on addressing the specific condition. For SVT episodes, the approach mirrors overall prevention: achieving optimal metabolic health. Cardiologists identify high blood pressure, sleep apnea, and excess weight as primary triggers for atrial fibrillation and flutter episodes.
Dr. Brewer lost approximately 8 pounds, which reduced his blood pressure and sleep apnea while making heart function easier. The same inflammatory processes affecting arterial walls also inflame atrial components.
Production challenges with caller audio systems were noted, with Jesus managing dual phone systems where one carries caller voice and the other does not.
Adam, age 72, experienced a possible TIA approximately one year prior. Symptoms included feeling drunk, dizzy, wobbly, with blurry vision lasting no more than five minutes. Following medical workup including CAC score of 370, brain MRI, echocardiogram, and Holter monitor, he was told findings were normal for his age. His C-reactive protein was elevated, and ApoB was high after he requested this test.
Adam began alternate-day fasting and completed several three-day fasts, reporting improved well-being and reduced blood pressure. He identified past alcohol consumption as likely contributing to insulin resistance and cardiovascular disease progression. His primary question concerns how to request tracking of arterial plaque progression from his cardiologist, specifically asking about CCTA with qualitative plaque analysis costs and Medicare coverage.
An AI bot was mentioned as providing 24/7 education on cardiovascular topics, eliminating the need to search through video content for specific information.
A TIA, or transient ischemic attack (ministroke), carries historical risk of subsequent permanent stroke with disability. Adam's proactive response to pursue testing and lifestyle modification was commended. The discussion emphasizes that lifestyle factors and insulin resistance, associated with aging, represent root causes that patients can address.
Patients must independently understand protective health information rather than relying on local physicians, as systemic pressures limit comprehensive care. This places significant responsibility on individuals until systemic changes occur.
Adam received a complimentary Heart Reveal Lab Panel, valued at approximately $500, designed to assess cardiovascular risk more comprehensively than standard lipid panels. The panel identifies inflammation from insulin resistance and other sources beyond high-sensitivity CRP. The package includes a one-on-one consultation to interpret results.
Alexander, age 46, received a calcium score of 34.3 and was prescribed 10mg statin, baby aspirin, and possibly creatine. He previously smoked from ages 15 to 30. A calcium score of zero indicates very low but not zero risk of plaque presence.
Smoking presents significant arterial risk. Each year after cessation, heart attack and stroke probability declines, approaching non-smoker levels after 7-8 years. Heart attacks and strokes kill more smokers than lung cancer.
Statins are recommended for known plaque rather than LDL levels alone. However, evidence is limited for patients who have achieved lifestyle optimization through carbohydrate reduction, weight loss, and metabolic improvement, particularly when CCTA with AI shows stable plaque. Lifestyle intervention represents the primary approach, though time constraints often lead physicians to prescribe medication without addressing root causes.
For a 40-year-old with positive calcium score, determining causation requires testing rather than speculation. Undiagnosed pre-diabetes is identified as the leading killer, making metabolic assessment the priority starting point.
Alexander expressed reluctance about starting 10mg statin. Dr. Brewer noted he typically prescribes lower doses, such as 5mg rosuvastatin, when initiating statin therapy for patients with newly discovered plaque.
Dr. Brewer started a low dose aspirin regimen over a decade ago but discontinued it after developing atrial fibrillation. He currently takes five grams of creatine daily, primarily for improving muscle and brain function rather than heart attack prevention. He emphasizes that muscle serves as the number one glucose sink and represents the primary protector against rising blood sugar for individuals 65 and older.
The producer offered Alexander an at-home glucose tolerance test to provide more comprehensive information about the root cause of metabolic issues, noting this represents one of the first recommended steps for patients.
Many patients report receiving only 15-minute appointments with practitioners who ultimately prescribe high-dose statins to lower LDL without addressing underlying lifestyle factors. Despite guidelines recognizing the importance of diet, exercise, sleep, and stress management, systemic issues prevent adequate time for lifestyle education, partly due to compensation structures that don't reward such comprehensive care.
Dr. Brewer is the only preventive medicine physician licensed in all 50 states and has personally trained practitioners and health coaches who provide detailed lifestyle guidance and create personalized plans. Patients interested in becoming prepmed patients can access services through a link in the video description.
Test, don't guess - Identify the root cause of metabolic issues before treatment.
Cut glycemic carbs - Reduce carbohydrate intake, particularly grain products that raise blood sugar more than sweets in most diets.
Add exercise with intensity - Beyond basic walking, incorporate hill sprints or intense walking when possible.
Remove roadblocks - Address stress and cortisol elevation, improve sleep quality, and consider sleep apnea screening even for thin individuals with BMI of 21. Simple interventions include trying side sleeping instead of back or stomach positions.
After initially viewing supplements as expensive urine during his Johns Hopkins training, Dr. Brewer discovered substantial evidence supporting supplements like berberine and vitamin D3 that he had previously overlooked. While lifestyle interventions should precede medications and supplements, both have appropriate roles, particularly for older adults where complete eradication of plaque and insulin resistance isn't realistic.
Discussion of emerging glycocalyx scanning devices that measure endothelial layer health. Current arterial function tests provide indirect reflections of glycocalyx function, but none have achieved sufficient accuracy, reliability, or predictability to serve as primary prevention tools.
Dr. Brewer shared his colonoscopy experience from 16 months prior where a polyp was identified but couldn't be fully accessed due to its position over a fold. Despite his medical background, he acknowledges the challenge of managing multiple preventive health measures and the tendency for recommended follow-ups to slip through the cracks.
A Saturday video will address vitamin D3 and K2 usage with new evidence-based guidance for arterial healing.
Growing old is not for sissies. I'm 69. I'm very much aware of it, but it's a lot better with healthy arteries.
Keep Dr. Ford Brewer MD MPH in your library
Save the videos and channels worth coming back to, and find them again in one place.