Your Beer Belly Is Killing You LITERALLY (Science Explains)
In a Nutshell
A big beer belly is driven primarily by visceral adipose tissue—an active, inflammatory fat depot around the organs that sharply raises the risk of diabetes, heart disease, stroke, and fatty liver. The fastest way to shrink it is a moderate, sustained caloric deficit plus high daily activity (8–12 k steps, cardio, lifting) and good sleep, while rapid weight cycling and low activity preferentially worsen visceral storage. GLP-1 drugs like tirzepatide accelerate the loss, but the key long-term fix is consistent moderate deficits, protein-rich diets, and ongoing movement rather than crash diets or sedentary restriction.
These notes were generated by AI and may contain inaccuracies.
The number one cause of having a big gut, specifically in a beer belly, is visceral adipose tissue. Visceral adipose tissue absolutely acts like a loud annoying organ in your body. It lies under the abdominal muscles, so it's nothing you can pinch. It can also lead to increased clotting tendency. If you have a big blood clot and it floats to the wrong part of your brain, you have a stroke. This is absolutely a cause of concern because it can literally kill you.
A beer belly is made of multiple components. Subcutaneous fat is the fat under your skin that you can pinch and move around. This can contribute to the beer gut look but is not the only factor. Another major component is having a loose abdominal wall, which is almost always genetic. This creates a hobbit look where you have a little belly even though you're not fat. The way to tell if it's a loose abdominal wall is if when you suck in and pull a vacuum, you can actually pull your waist in super tight, but then when you relax, it goes back to normal.
Several temporary factors can cause belly distension. These include eating a big meal with more volume in your stomach and intestines, carbonated drinks creating gas volume and fluid volume, certain foods fermenting more in the gut due to different gut microbiota, sugar alcohols, certain high-fiber foods, and some dairy foods for people who are sensitive. General food sensitivities can also contribute. Constipation and slow digestion from eating large amounts of fat, fiber, and protein can make the gut big temporarily. Low daily movement contributes to slow gut movement.
Water retention can bloat up your whole body and gut. High salt meals with lots of fluids can temporarily pull water in. Big carb days also cause temporary water retention. Inflammation from stress, poor sleep, alcohol, and hard training without enough recovery can make you look puffier all over including in your belly. Chronic long-term systemic inflammation can cause more fluid or swelling plus slower digestion. Some people get notably distended abdomens during periods of poor sleep, high stress, and sometimes after trigger foods.
Posture and rib cage position can affect how the gut looks. When you have anterior pelvic tilt and your ribs are flared, it creates a pregnant look. However, posture is very difficult to fix normally, and the way you're walking through the world when relaxed is going to be your default genetic state. Posture improvements are small and take months according to most literature.
Serious medical conditions can cause abdominal swelling, fluid buildup, and tumors. Digestion can stop with conditions like gastroparesis. If belly size changes rapidly with pain when you don't normally have a gut, see a doctor immediately because there's a one in a thousand to one in ten thousand chance something serious is happening.
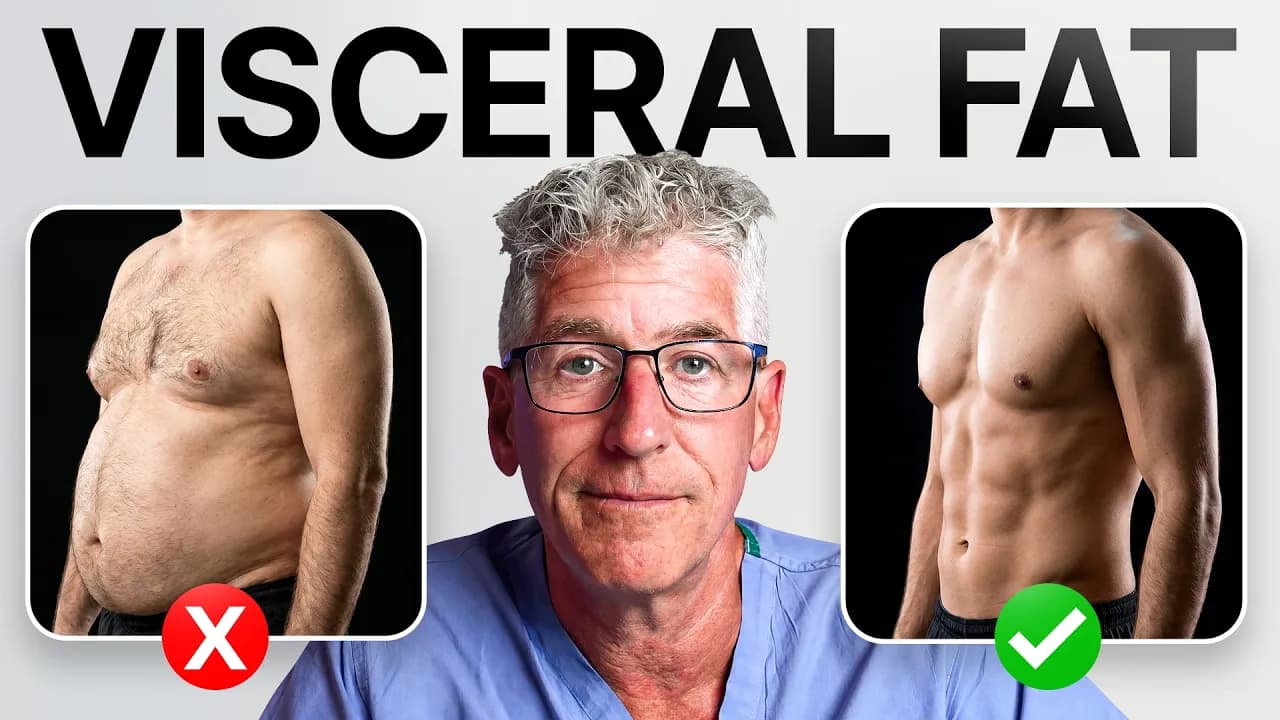
Visceral adipose tissue is the fat lying between your organs, between folds of your intestines, around your liver, and even around your heart. It lies under the abdominal muscles so nothing you can pinch. Even with a six-pack visible, you can have protruding belly from VAT with almost no subcutaneous fat to pinch. This fat is packed around organs everywhere, resulting in a look where you may not have folding fat from behind or front, but when you turn to the side, there's belly.
VAT increases primarily through caloric surplus. When you have a caloric surplus, calories can go to building muscle if training hard, subcutaneous fat, brown fat deposits, or visceral adipose tissue. What decides where fat goes includes genetics as the primary factor. Your fat storage map determines patterns - some people store fat in butt, hips, arms, or under chest, while others store more in the gut. Sex and hormonal environment also matter, with high estrogen favoring lower body storage and lower estrogen or lower testosterone associated with more central and visceral fat gain.
How expandable your subcutaneous fat storage is matters. If you don't have many fat cells under the skin because you've never been super fat, rapid overeating can fill subcutaneous storage and then excess goes to visceral fat. The pace of weight increase matters significantly. Rapid weight regain tends to cause messier storage with higher likelihood of ending up in less ideal places including visceral adipose tissue. After dieting and getting lean, rapid weight regain causes more visceral storage than usual.
High activity level makes you less prone to visceral adipose tissue storage during fat gain, with more going to subcutaneous fat. When losing weight, high activity through 8-10-12,000 steps daily plus cardio and lifting burns preferentially visceral adipose tissue. Low activity weight loss results in more subcutaneous fat loss, while high activity results in more visceral fat loss even at the same total weight lost. Endurance runners almost never have big guts due to high activity levels.
Highly processed diets make overeating easier, increasing rapid weight gain and thus more visceral storage. They also worsen blood sugar control and lead to acute or chronic inflammation increases. Chronically inflamed individuals store more fat in visceral adipose tissue. High alcohol intake couples surplus calories with worse sleep and more liver stress, leading to more liver fat storage which is a component of visceral adipose tissue.
Poor sleep and chronic stress shift appetite upwards and worsen how the body handles incoming calories, with less going to muscle and more to visceral adipose tissue. Nicotine consumption through smoking or other means can suppress appetite but is associated with more central fat patterning. Some medications increase appetite or change nutrient handling, increasing central visceral fat gain. Corticosteroid medications like prednisone and cortisone can visibly impact visceral adipose tissue even during short-term use, and chronic use increases visceral storage significantly.
Chronic sleep restriction during bulking phases increases visceral adipose tissue deposition. Sleep restriction makes you hungrier, less satisfied after meals, more snack prone, and worsens blood sugar control acutely, biasing toward midsection storage over time. High quality sleep reduces the probability of gaining significant visceral adipose tissue during weight gain phases.
High chronic stress means you gain less muscle and lose it faster, gain more fat overall, and gain more of that fat inside the gut. Stress hormones like cortisol have similar intra-abdominal fat storage effects as medical corticosteroids, though at lower doses. A year or two of high stress combined with weight gain creates significant visceral adipose tissue accumulation.
A year or two of high stress combined with gaining weight is a recipe for developing a beer gut. A sedentary lifestyle with low daily movement contributes significantly, as sitting frequently without substantial walking reduces the preferential burning of visceral adipose tissue during exercise. Even with caloric restriction, low physical activity results in less gut fat loss than expected.
High alcohol intake builds fat specifically around the liver, increasing visceral adipose tissue while reducing overall body health and substrate handling, creating a compounding effect. Ultra-processed foods contribute through chronic inflammation when consumed regularly, and their high palatability leads to overconsumption, making it easy to exceed caloric needs.
Low protein diets impair hunger control, while low fiber intake reduces fullness signals, promoting increased eating. Weight cycling through repeated loss and regain, particularly via caloric restriction without increased physical activity, causes disproportionate visceral adipose tissue accumulation. During weight loss phases without adequate exercise, subcutaneous fat reduces more than visceral fat, but upon weight regain, visceral stores increase disproportionately. Rapid cycling with minimal activity and severe caloric restriction accelerates this process.
Steroid medications and psychiatric medications contribute to visceral fat accumulation. Untreated sleep apnea increases cortisol levels through nighttime breathing difficulties, elevating visceral adipose tissue risk.
Visceral adipose tissue increases with age independently of scale weight changes. Muscle loss combined with fat gain occurs gradually due to reduced activity and lack of weight training. Chronic stress, inflammatory states, and aging effects independently increase intra-abdominal fat storage. This creates the characteristic silhouette difference between younger and older individuals, with older people storing fat more centrally.
Menopause shifts fat storage toward the abdomen in women. Lower testosterone levels in men similarly affect distribution patterns. Hormone replacement therapy can address these changes, but unaddressed aging processes allow incremental gut growth over time. Even maintaining the same scale weight from younger years results in different body composition, with fat redistributing from limbs to trunk.
Poor sleep and high stress, often normalized as inherent to adulthood, significantly contribute to visceral adipose tissue accumulation. Older adults who lose weight tend to regain it rapidly, compounding the visceral fat problem.
Visceral adipose tissue correlates with higher fasting blood sugar, elevated average blood glucose over time, and increased insulin levels. Insulin resistance develops as cells require more insulin signaling for nutrient uptake, raising type 2 diabetes probability. Blood lipid profiles worsen with higher triglycerides, elevated LDL cholesterol, and reduced HDL cholesterol.
Higher blood pressure frequently accompanies central fat accumulation. Fatty liver risk increases, with non-alcoholic fatty liver disease presenting serious metabolic consequences. Systemic inflammation rises while cardiorespiratory fitness typically declines due to associated inactivity patterns.
Sleep apnea risk increases through belly and neck fat affecting nighttime breathing, creating a feedback loop where sleep apnea promotes further visceral fat gain. This can manifest as normal weight but metabolically unhealthy individuals.
Visceral adipose tissue functions as an active endocrine organ rather than inert energy storage, releasing inflammatory chemical signals that increase whole-body inflammation. This inflammation promotes insulin resistance and can lead to type 2 diabetes. Hyperinsulinemia from chronic elevated insulin levels creates significant health problems.
Increased nutrient delivery to the liver promotes fatty liver growth and non-alcoholic fatty liver disease development. The liver responds by producing more triglyceride-rich particles, damaging cardiovascular health. Blood pressure elevation occurs through hormonal effects, damaging organs, nerves, eyes, and kidneys while increasing heart disease and stroke risk.
Kidney damage probability increases alongside elevated clotting tendency, raising stroke risk from blood clots. Sleep quality deteriorates through discomfort, inflammation, and poor metabolic regulation beyond sleep apnea effects alone.
Visceral adipose tissue ranks among the strongest predictors of cardiovascular disease risk through worsening blood sugar, blood lipids, blood pressure, and inflammation.
Reducing visceral adipose tissue improves blood sugar control, lowers insulin levels, and enhances insulin sensitivity. Triglycerides decrease while lipid handling improves overall. LDL cholesterol drops while HDL cholesterol rises. Liver fat reduction provides systemic health benefits.
Chronic inflammation decreases substantially. Blood pressure often reduces modestly but meaningfully over time. Weight loss from visceral stores improves nighttime breathing, sometimes dramatically enhancing sleep quality.
A positive feedback loop emerges where visceral fat reduction makes further reductions more likely, while increases promote additional accumulation. Significant risk reduction occurs early in weight loss without requiring extreme leanness. Going from high to moderate visceral fat levels provides substantial health improvements.
Traditional rapid dieting with low physical activity loses more subcutaneous than visceral fat, with weight regain disproportionately returning to visceral stores. Moderate, sustained caloric deficits over extended periods prove more effective than aggressive short-term approaches.
Higher protein intake preserves muscle mass during weight training while improving satiety. Adequate fiber and overall food quality support healthy dieting. Avoiding excessively rapid weight loss prevents fatigue that makes visceral fat more resistant to reduction.
Exercise creates caloric deficits while preferentially targeting visceral adipose tissue. Brisk walking, cycling, running, and rowing show strong associations with lower visceral fat. Higher intensity cardio provides additional benefits. Strength training increases muscle mass, supporting metabolic health that discourages visceral fat retention.
Daily step counts of 8,000-12,000 combined with consistent physical activity effectively target visceral fat. Long-term exercise reduces overall stress and systemic inflammation when recovery is properly managed.
Quality sleep during fat loss phases promotes greater visceral adipose tissue reduction. Alcohol elimination or significant reduction supports the process.
Tirzepatide and retatrutide demonstrate superior visceral adipose tissue reduction compared to subcutaneous fat loss. These medications create smaller waist measurements earlier in the process while subcutaneous fat reduces more gradually.
Long-term use over months and years allows visceral adipose tissue to shrink chronically through repeated cycles of reduction during dieting phases with minimal regain during maintenance or muscle-building phases. This contrasts with traditional weight cycling patterns that increase visceral fat fractions over time.
These medications require medical supervision and prescription. Retatrutide remains in phase three trials with potential approval in 2026. Proper medical oversight minimizes side effects while maximizing benefits.
DEXA scans provide the most accurate visceral adipose tissue measurements alongside body fat percentage, distribution analysis, and bone mass data. Regular tracking allows monitoring of visceral fat changes over time, particularly valuable for lean individuals who may still carry elevated visceral adipose tissue levels.
Your health serves as an important underpinning factor for aesthetics even if the primary goal is to look good rather than feel good. Poor health, systemic chronic inflammation, and excessive visceral adipose tissue directly make people look worse through effects on skin quality, hair condition, posture, and overall demeanor. Fat distribution becomes less favorable with a bigger gut, creating a worse aesthetic appearance. Poor health literally makes you look bad.
Good health functions as the foundation for high throughput physical activity and recovery. People in bad health cannot perform substantial exercise and cannot recover effectively from training. Those in good health can handle large amounts of exercise and recover efficiently. Good health serves as the engine that enables aesthetic changes through diet, training, and sleep optimization.
The relationship between health and aesthetics mirrors how going to work and earning income enables fun at night - they're not directly related but connected by one logical step. Better health directly improves appearance while also enabling the consistent behaviors that produce even better aesthetic results over time.
When getting leaner and checking body fat with a DEXA scan, consider using the RP Diet Coach app to organize an intelligent diet plan. The RP hypertrophy app helps preserve muscle, improve appearance, increase health, and decrease visceral adipose tissue. Get a DEXA scan to track visceral adipose tissue approximately every year at the same phase of fat loss or weight gain cycles. The goal is to reduce visceral adipose tissue to the very low risk category over time.
Having a lean and muscular physique while carrying substantial visceral adipose tissue remains a serious health concern because it can literally kill you. The RP hypertrophy app is available in the App Store.
Keep Renaissance Periodization in your library
Save the videos and channels worth coming back to, and find them again in one place.